
Data snapshot and why it matters
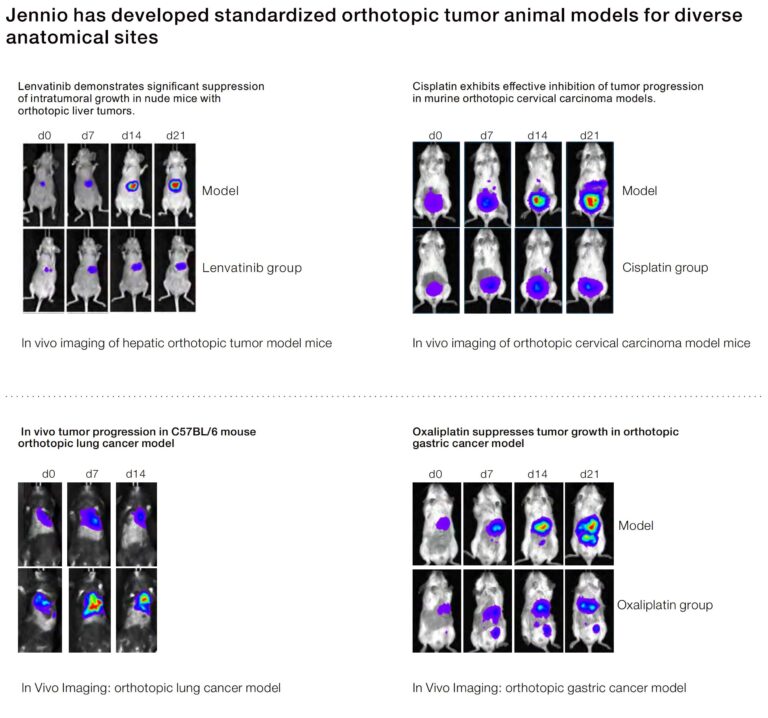
Drug teams burn months chasing false leads because models don’t mimic real tumors. Labs in the Boston–Cambridge biotech cluster use orthotopic placements to get closer to human biology, and that shift shows up in shorter lead cycles and cleaner go/no-go decisions. One practical tool many groups turn to is the orthotopic tumor model, which preserves tumor microenvironment cues and often improves engraftment efficiency versus subcutaneous setups.
Why orthotopic models change the equation
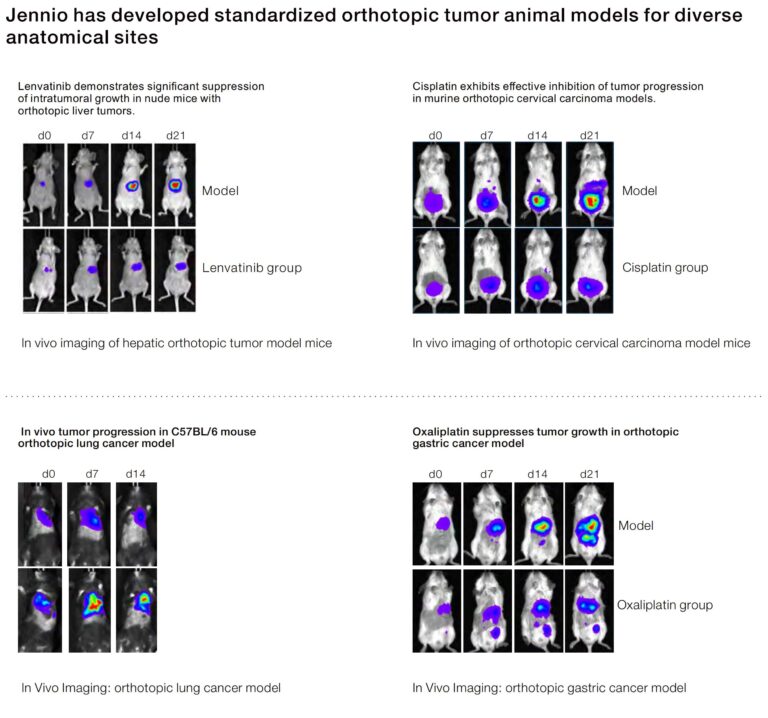
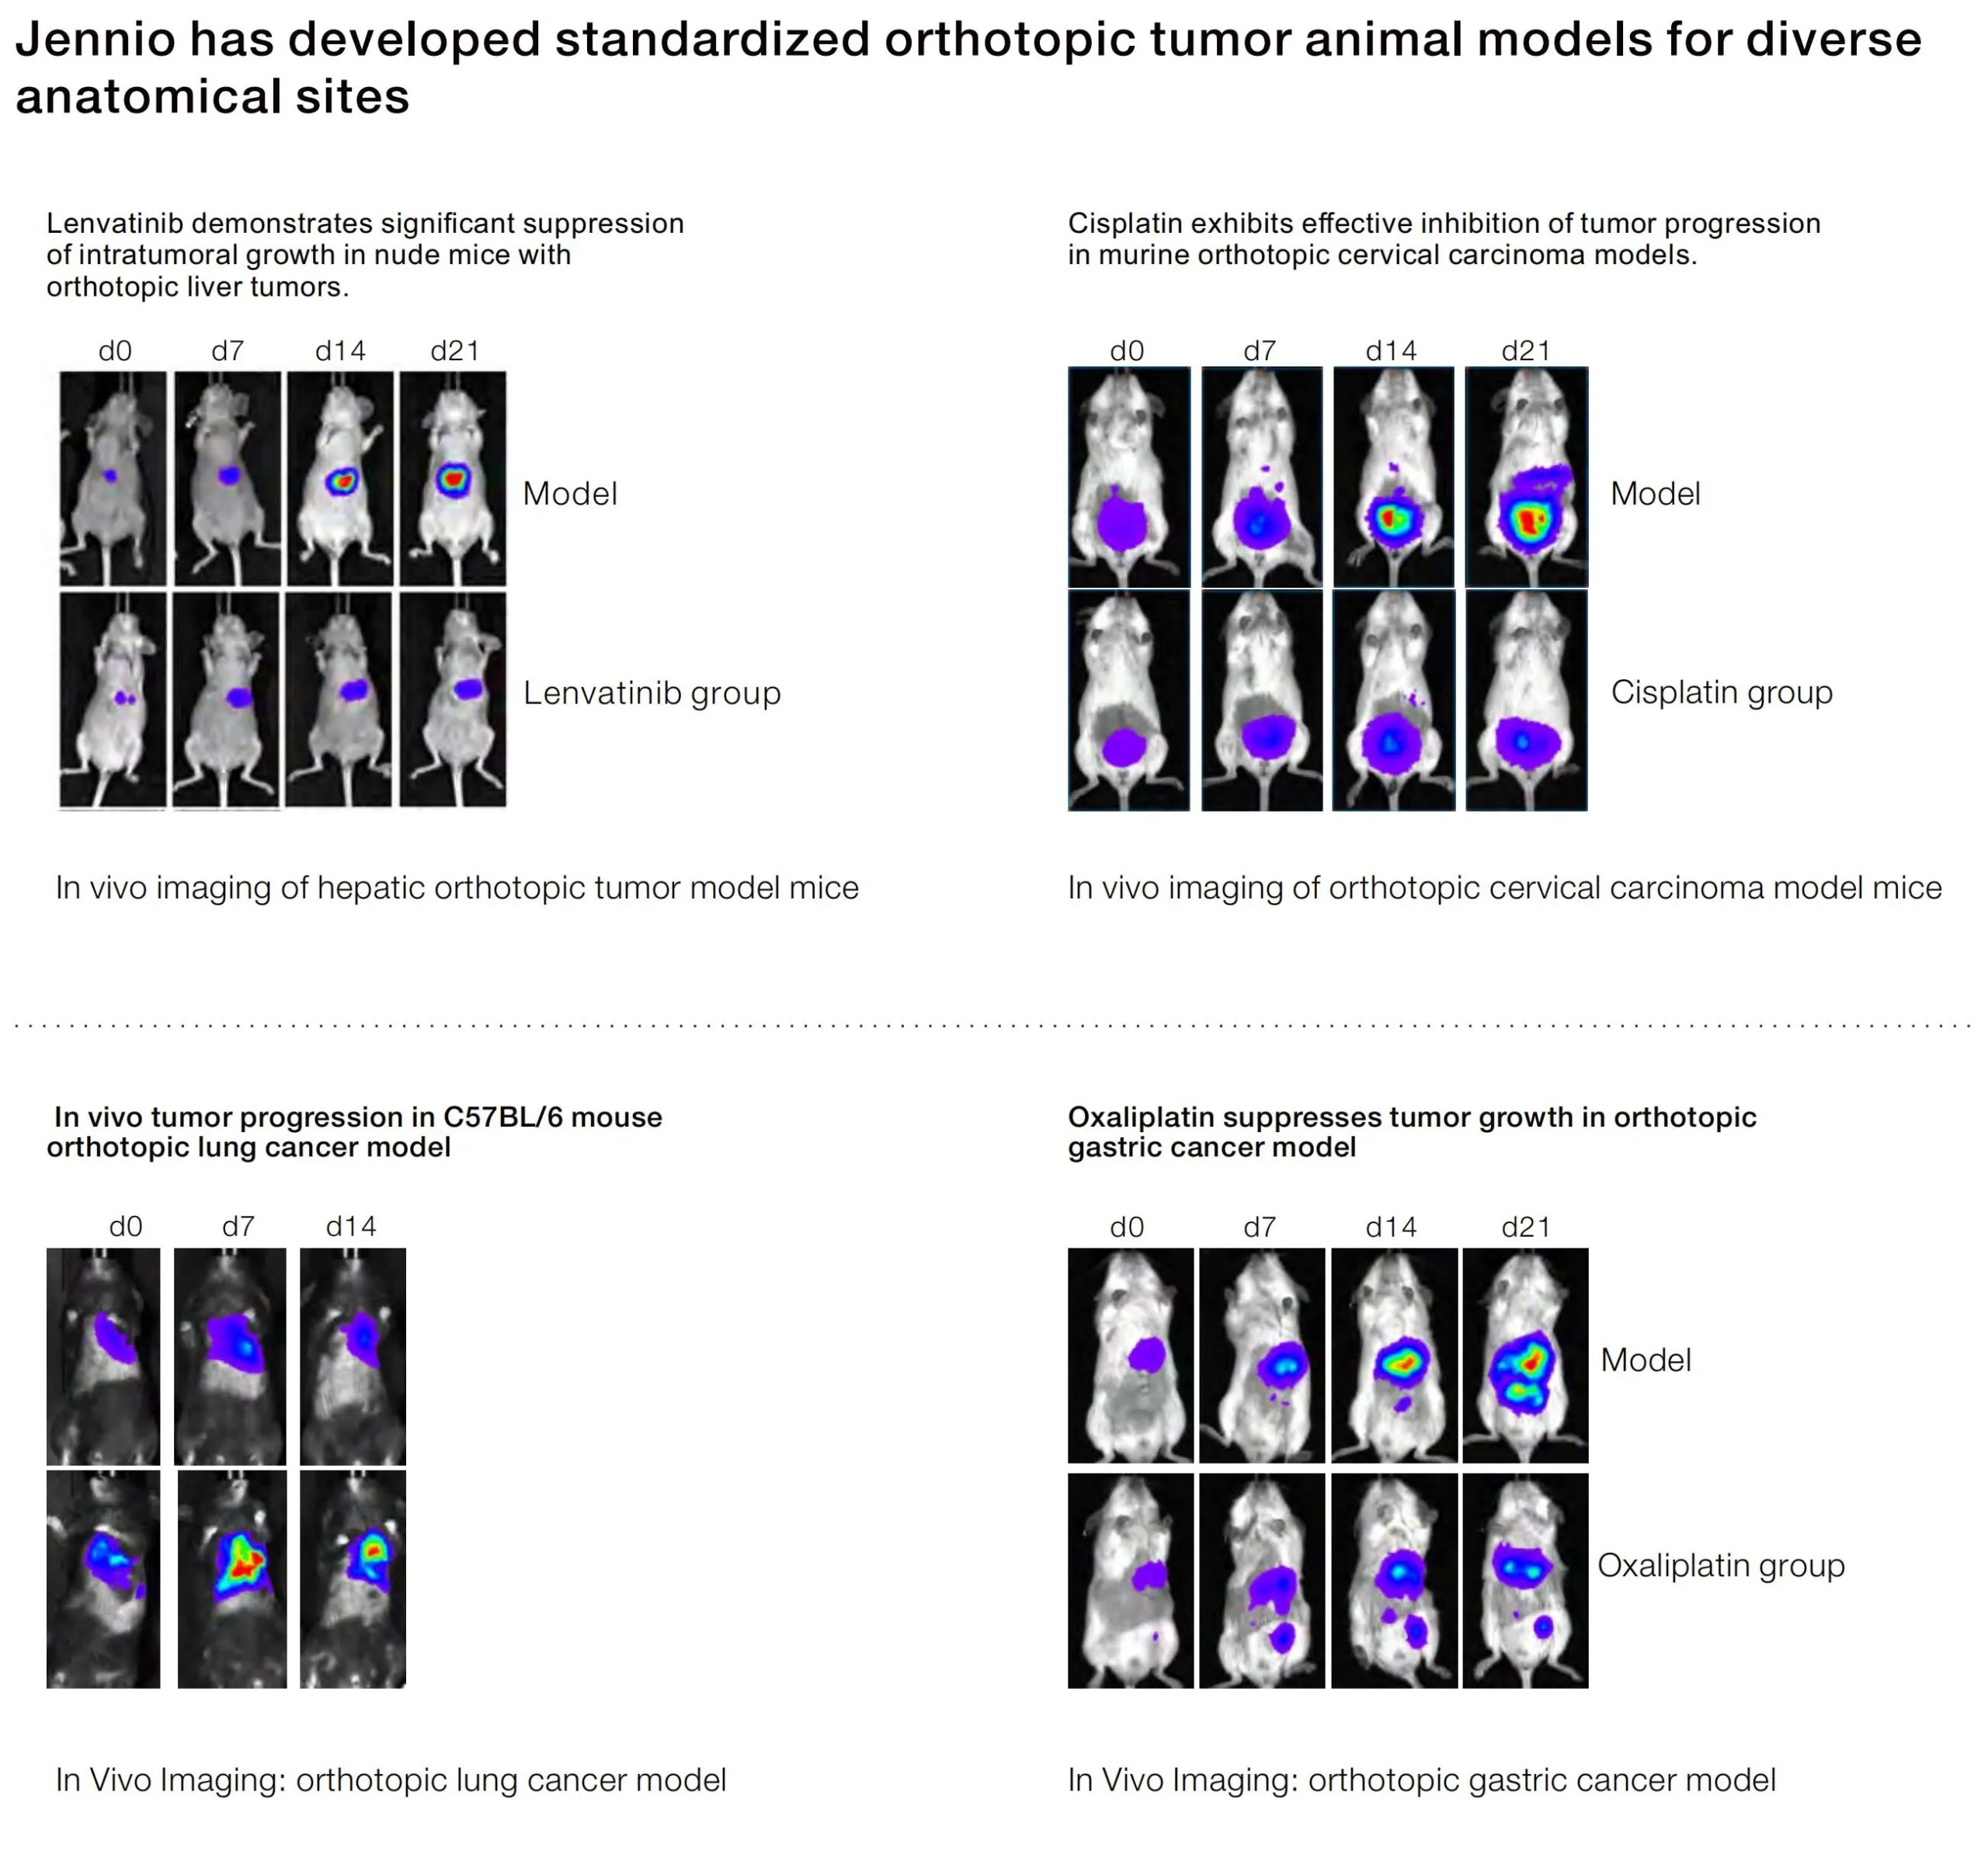
Orthotopic xenografts put cancer cells where they belong — liver cells into liver, lung into lung — so you test drugs against relevant stromal interactions and metastatic routes. That’s huge: pharmacodynamics and responses to immune-modulating agents differ by site. Using orthotopic implantation and PDXs (patient-derived xenograft) reduces misleading efficacy signals and helps teams prioritize leads that behave like clinical tumors. Bioluminescence imaging (BLI) and metastatic models then give timelines that match translational endpoints better.
How teams actually save time: observed patterns
Across practical projects, three patterns repeat:
– Early filtering with orthotopic models cuts downstream failures by revealing site-specific resistance mechanisms.
– Quantitative endpoints from tumor microenvironment readouts speed decision meetings; you get a number, not a hunch.
– Integrating pharmacokinetics with orthotopic response data aligns dosing strategies before IND-enabling studies, so toxicology packages are less likely to need rework.
These patterns come from work done in established hubs like Cambridge, MA and multiple translational labs that compared subcutaneous and orthotopic cohorts—real-world practice beats assumptions. — small teams especially see faster pivots when they trust model-based data early.
Operational production teardown
Runbook, trimmed: source tumor tissue, prepare orthotopic implant, verify engraftment with BLI, harvest endpoint tissues for histology and molecular profiling. For consistency, include explicit QC steps: viability threshold (≥85% live cells pre-implant), implantation depth standard (2–3 mm depending on organ), and engraftment check at day 7 and day 21 with imaging. In the production teardown you should track {main_keyword} and {variation_keyword} alongside engraftment efficiency and time-to-signal so ops and science speak the same metrics.
Common mistakes and quick fixes
Teams often underestimate surgical consistency and readout timing. Fixes that pay off fast:
– Standardize implantation protocol and log deviations.
– Use matched controls for microenvironmental factors, not just cell line controls.
– Build a simple dashboard combining BLI flux, tumor volume, and plasma PK so chem and bio talk in the same units.
Three golden rules for trustable preclinical speed (Advisory)
1) Prioritize predictive endpoints: pick readouts that matched later clinical biomarkers in past program history. Measure response kinetics and not only end-volume. 2) Insist on site-appropriate models: orthotopic xenograft tumor model data must be part of any go/no-go before GLP tox. 3) Track operational fidelity: log implantation variance, imaging cadence, and engraftment rate; reject datasets where engraftment <70% or imaging intervals vary by more than ±20%.
Closing thought
Applying these rules shortens cycles and raises confidence — faster decisions, fewer blind alleys. For groups that need consistent, translational tumor platforms, partnering with labs that deliver reproducible orthotopic outputs saves calendar time and budget. Jennio Biotech brings that practical reliability into studies, making model-driven timelines a steady advantage — a clear cut for teams that want predictable progress.
—